When Two Infections Enter the Room: The Clinical Blind Spot of Simultaneous Pathogen Exposure
The One-Pathogen Assumption That Shapes Everything
When a patient walks into an emergency department with fever, shortness of breath, and a productive cough, the clinical process that follows is largely linear. A physician gathers symptoms, orders targeted tests, and pursues a diagnosis built around identifying a single responsible pathogen. This approach is not arbitrary—it reflects decades of diagnostic tradition, guideline development, and the way medical education trains clinicians to think. Find the cause. Treat the cause. Resolve the illness.
The problem is that biology does not always cooperate with this framework. An increasing body of clinical evidence suggests that simultaneous infections—cases in which a patient harbors two or more distinct pathogens at the same time—are far more common than standard diagnostic pipelines are designed to detect. And when they go unrecognized, the consequences can range from prolonged illness to dramatically elevated mortality.
Coinfections are not a new phenomenon. What is new is the growing clinical awareness that medicine's single-pathogen model may be systematically underserving patients whose bodies are fighting on more than one front.
What Coinfection Actually Looks Like
The term coinfection covers a broad clinical territory. At one end of the spectrum are well-documented combinations—HIV and tuberculosis, for instance, or Lyme disease and babesiosis transmitted by the same tick bite. These pairings have established clinical protocols precisely because the medical community has had decades to recognize their frequency and consequences.
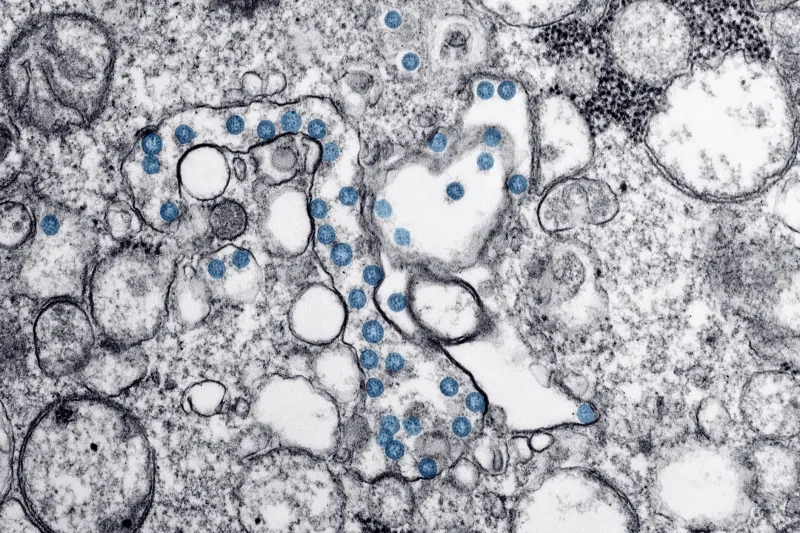
At the other end are less codified combinations that emerge in real time during respiratory illness seasons. During the COVID-19 pandemic, clinicians began documenting patients who tested positive for SARS-CoV-2 while simultaneously harboring bacterial pneumonia, influenza A, or respiratory syncytial virus (RSV). Some of these patients had already been triaged and treated under the assumption that COVID-19 alone explained their presentation. When the secondary pathogen was eventually identified, treatment regimens had to be reconsidered—sometimes urgently.
In pediatric settings, coinfections involving RSV and rhinovirus, or influenza and Streptococcus pneumoniae, have been associated with more severe disease courses than either infection typically produces in isolation. A child admitted for what appears to be a straightforward RSV bronchiolitis may be carrying a bacterial co-pathogen that transforms a manageable hospitalization into a critical one.
Why Diagnostic Systems Are Poorly Designed for Complexity
The architecture of clinical diagnostics in the United States is largely built around ruling in or ruling out specific pathogens in sequence. When a rapid influenza test returns positive, many clinical workflows effectively terminate the diagnostic search. The physician has found an explanation. The treatment algorithm activates. The possibility that a second—or third—pathogen is simultaneously active often goes unexplored.
This is partly a matter of resources. Comprehensive multiplex testing panels, which can screen for dozens of pathogens from a single respiratory sample, exist and are increasingly available. But they are not universally deployed, and their use is often reserved for immunocompromised patients or cases that have already deteriorated beyond initial management. For patients who present with moderate illness, the clinical calculus frequently does not support the additional cost and processing time of broad-spectrum testing.
Guidelines issued by major professional bodies—including those from the Infectious Diseases Society of America and the Centers for Disease Control and Prevention—are themselves largely organized around single-pathogen management. These documents are rigorously developed and evidence-based, but their evidence base is drawn primarily from studies that enrolled patients with confirmed single infections. When a patient's actual presentation involves two overlapping pathogens, the clinical guidance may not fully apply.
How Coinfections Alter Disease Severity
The clinical significance of coinfection extends well beyond the inconvenience of a missed diagnosis. When two pathogens occupy the same host simultaneously, their biological interactions can amplify harm in ways that neither would produce independently.
Influenza, for example, damages the mucosal lining of the respiratory tract in ways that create favorable conditions for secondary bacterial invasion. This is why bacterial pneumonia following influenza infection has historically been a major driver of influenza-related mortality—including during the 1918 pandemic, where many deaths attributable to influenza were in fact the result of subsequent bacterial infections. Modern antibiotic availability has reduced this risk, but the underlying biological dynamic remains.
More recently, researchers studying COVID-19 outcomes found that patients who developed bacterial coinfections during hospitalization faced substantially higher rates of intensive care admission and mechanical ventilation than those with COVID-19 alone. The immune dysregulation associated with severe SARS-CoV-2 infection appears to lower resistance to opportunistic bacterial pathogens, creating a compounding effect that neither the viral nor bacterial component alone would have produced.
For patients with underlying immunocompromise—whether from HIV, chemotherapy, organ transplantation, or certain autoimmune therapies—the coinfection risk is even more pronounced. These individuals may simultaneously carry fungal, viral, and bacterial pathogens, each exploiting the same immunological gaps. The clinical picture that results can be extraordinarily difficult to interpret and even harder to treat.
The Treatment Dilemma No Protocol Fully Addresses
Even when coinfection is correctly identified, the treatment phase introduces its own set of complications. Antiviral agents, antibiotics, and antifungals each carry their own side effect profiles and drug interaction risks. When multiple agents are needed simultaneously, the potential for adverse interactions rises, and the therapeutic margin narrows.
Physicians treating coinfected patients must also navigate the reality that treating one infection aggressively may temporarily worsen the other. Immune reconstitution inflammatory syndrome—a phenomenon observed in HIV-positive patients initiating antiretroviral therapy—occurs when a recovering immune system mounts an exaggerated response to a previously quiescent coinfection, sometimes causing dangerous inflammation. This is a known risk, but it illustrates how the treatment of one pathogen can destabilize the equilibrium surrounding another.
These clinical complexities rarely appear in standard treatment algorithms, which are designed to offer actionable guidance for the most common presentations. The patient with two simultaneous infections occupies a clinical gray zone that requires experienced judgment, specialist consultation, and often a degree of improvisation that guideline-based medicine was not designed to accommodate.
Closing the Gap Between Clinical Reality and Medical Frameworks
Addressing the coinfection blind spot will require changes at multiple levels of the medical system. At the diagnostic level, broader deployment of multiplex testing—particularly during respiratory illness seasons when pathogen co-circulation is highest—would allow clinicians to identify complex infections before treatment decisions are locked in. At the research level, clinical trials that deliberately enroll coinfected patients, rather than excluding them as confounders, would generate evidence that better reflects what clinicians actually encounter.
At the educational level, medical training programs have an opportunity to explicitly incorporate coinfection recognition into the clinical reasoning frameworks taught to students and residents. The instinct to find a single explanation for a patient's symptoms is deeply ingrained—and often correct—but it should be accompanied by a trained awareness of when the clinical picture is too complex to fit a single-pathogen model.
For patients, the practical implication is less about demanding specific tests and more about communicating fully with their care team when symptoms seem unusually severe, when they deteriorate after an initial period of improvement, or when they have known exposures to multiple illness sources. These details can prompt the clinical curiosity that a busy diagnostic workflow might otherwise suppress.
The assumption that one patient carries one infection at a time has served medicine well in many contexts. But as the clinical evidence accumulates, it is becoming clear that this assumption has limits—and that patients whose infections fall outside those limits deserve a medical framework equipped to find them.