Testing Everyone, Helping Fewer: The Hidden Costs of America's Asymptomatic Screening Ambitions

The Promise That Launched a Thousand Swabs
For decades, American public health strategy has operated on a deceptively simple premise: finding an infection earlier is always better than finding it later. This logic underpinned the expansion of routine chlamydia screening in sexually active women under 25, universal hepatitis C testing for adults born between 1945 and 1965, and the sweeping COVID-19 surveillance apparatus that emerged after 2020. Each initiative arrived with compelling data, institutional backing, and the moral authority of prevention science.
Yet a quieter conversation has been building within epidemiology and clinical medicine — one that asks whether the relentless pursuit of every detectable pathogen in populations that feel entirely well has begun to generate harms that rarely appear in the press releases announcing these programs.
What Overdiagnosis Actually Means in Infectious Disease
Overdiagnosis is a concept more familiar in oncology than in infectious disease. When applied to cancer, it describes the detection of tumors that would never have caused symptoms or death during a patient's lifetime. The parallel in infectious disease is less intuitive but no less real: not every detectable infection is a clinically meaningful one.
Consider hepatitis C. The universal screening recommendation issued by the U.S. Preventive Services Task Force in 2020 expanded testing to all adults aged 18 to 79, regardless of risk factors. The rationale was sound — effective antiviral treatments exist, and untreated chronic infection can progress to cirrhosis or liver cancer. But studies examining screened populations have consistently found a subset of individuals with detectable viral RNA who, absent any intervention, would likely never develop significant liver disease. Identifying these patients draws them into treatment pipelines that carry their own risks, including drug interactions, financial burdens, and the psychological weight of a chronic disease diagnosis.
The situation becomes more complex when the pathogen in question resolves spontaneously in a significant proportion of those infected. Roughly 25 to 45 percent of people infected with hepatitis C clear the virus on their own without treatment. Screening cannot reliably distinguish in advance who will clear the infection and who will not, which means that some portion of screened individuals receive diagnoses — and potentially treatment — for a condition their immune systems were already managing.
Chlamydia and the Cascade Problem
Chlamydia screening in young women presents a different but equally instructive set of trade-offs. Annual screening for sexually active women under 25 is recommended by multiple major health organizations and has been standard practice in many clinical settings for years. The justification centers on preventing pelvic inflammatory disease (PID) and its downstream consequences, including infertility and ectopic pregnancy.
However, the evidence linking asymptomatic chlamydia to PID is more nuanced than screening guidelines often convey. A substantial proportion of untreated chlamydial infections resolve without clinical consequence. More concerning, a positive screening result frequently initiates what clinicians call a treatment cascade — a sequence of events that can include antibiotic courses, partner notification, repeat testing, anxiety, and in some cases, relationship harm, all stemming from an infection that may have resolved on its own within months.
Antibiotic treatment for chlamydia carries its own downstream implications. In an era defined by antimicrobial resistance, the routine prescription of azithromycin or doxycycline to populations of asymptomatic individuals contributes incrementally to selective pressure on bacterial populations — a cost that is diffuse, difficult to measure, and rarely attributed to screening policy.
COVID-19 Testing and the Anxiety Infrastructure
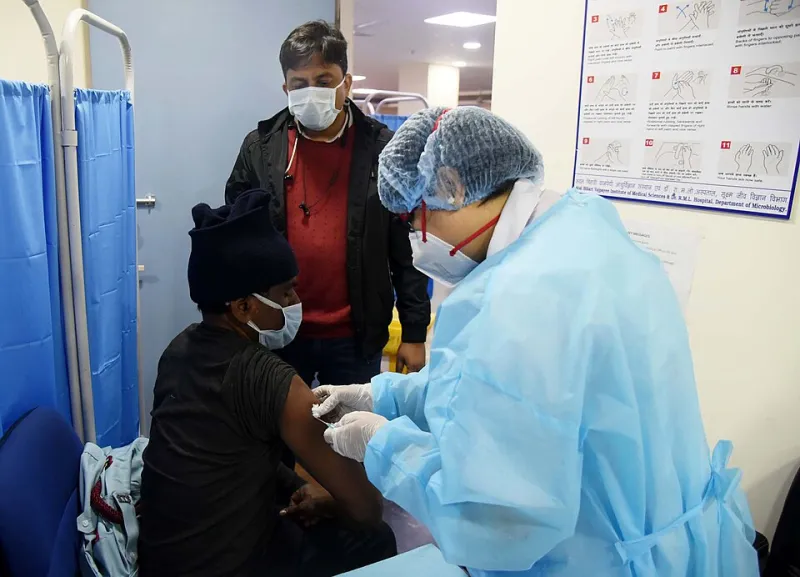
The COVID-19 pandemic accelerated asymptomatic screening to an unprecedented scale. At the peak of the testing infrastructure, millions of Americans were tested weekly — in schools, workplaces, airports, and pharmacies — regardless of symptom status. The public health rationale was clear: identifying and isolating asymptomatic carriers could interrupt transmission chains and protect vulnerable populations.
What received less attention was the psychological infrastructure that mass testing created. Studies conducted during and after the acute pandemic phase documented elevated rates of health anxiety among individuals subjected to repeated testing, particularly those who received positive results while feeling well. For many, a positive test without symptoms created a cognitive dissonance that proved difficult to resolve — they had been told they were infected, yet they felt entirely normal. This dissonance, repeated across millions of Americans, contributed to a broader erosion of trust in both testing accuracy and public health communication.
False positives, while relatively rare with PCR-based platforms, were not negligible at the scale of mass deployment. A test with 99 percent specificity administered to 10 million people generates approximately 100,000 false positive results — each one capable of initiating quarantine, job disruption, and medical follow-up for someone who was never infected.
The Equity Dimension Rarely Discussed
Screening programs also carry an equity dimension that public health advocates have been slow to confront directly. The burden of follow-up testing, treatment, and lost work time associated with a positive screening result does not fall equally across the population. Lower-income Americans, those without paid sick leave, and individuals in communities with limited healthcare access bear a disproportionate share of the downstream consequences when a screening program generates a positive result that requires further management.
When a universal screening recommendation is issued without commensurate investment in the infrastructure needed to support those who test positive — including affordable treatment, counseling, and follow-up care — the program effectively transfers burden onto the populations it was designed to protect.
Rethinking the Calculus
None of this is an argument against screening. Early detection of infectious disease has unambiguously saved lives. Hepatitis C treatment, when appropriately indicated, prevents liver failure and cancer. Chlamydia treatment prevents some cases of PID. COVID-19 testing enabled targeted interventions that reduced transmission in high-risk settings.
The argument is more precise: that the automatic equation of more testing with better outcomes deserves scrutiny, and that public health policy should be designed with as much attention to the harms of detection as to the benefits. Risk stratification — directing intensive screening toward populations with genuine elevated risk rather than applying universal mandates — represents one evidence-based approach that several researchers have advocated for years.
Transparency in public communication is equally important. When health agencies recommend screening, they are making a probabilistic judgment on behalf of a population. Patients deserve to understand not only what a positive result might mean, but also what it might not mean — including the realistic possibility that their immune system is already handling the situation without intervention.
A More Honest Public Health Conversation
American medicine has long been more comfortable with action than restraint. The directive to test, treat, and follow up feels responsible in a way that watchful waiting rarely does, particularly in the context of infectious disease, where the specter of transmission adds moral urgency to clinical decision-making.
But responsible public health policy requires honesty about trade-offs. Screening programs that detect infections in people who would never become ill, that generate cascades of treatment with their own risks, and that impose disproportionate burdens on vulnerable populations are not neutral interventions. They are policies with consequences — and those consequences deserve the same rigorous, evidence-based scrutiny that we apply to the diseases they are designed to prevent.